Jennifer McLaren, MD
Overview
This section provides a brief overview of depressive disorders in people with intellectual and developmental disability (IDD) and autism spectrum disorders (ASD). Depressive disorders are common among people with IDD with lifetime prevalence rates of 37%.1 Common antecedents for depression in people with IDD include personal loss (e.g., caregiver, friend, staff), isolation, marginalization, lack of autonomy, trauma, bullying, victimization, or other adverse experiences. It is important to ask about these losses as they should impact the therapeutic intervention chosen.
Assessment
The core features of depressive disorders are a depressed and/or irritable mood with a marked change from a person’s baseline and impairment in functioning.1,2 The severity of a person’s ID impacts their presentation of depression. People with mild to moderate ID may report feeling sad or depressed, making depression easier to recognize. People with a more significant intellectual impairment may not verbalize their internal feelings, making a depression diagnosis more nuanced.3For all people, observation of presentation and collateral information are key.
The diagnosis of depressive disorders requires meeting current diagnostic criteria for one of the following: disruptive mood dysregulation disorder, major depressive disorder, persistent depressive disorder, pre-menstrual dysphoric disorder, other specified and unspecified depressive disorders, and depressive disorder due to another medical condition.1 These disorders are frequently comorbid with anxiety disorders. Consider utilizing a standardized rating scale when assessing and treating depression such as the PHQ-9.4 Adaptations to the PHQ-9 have been made for people with IDD.
For moderate to severe depression, consider a combination of therapy plus antidepressants.6,7 There is a lack of research on psychopharmacologic treatments for people with depression and IDD.8 Psychotropic medications to treat depression in the general population are utilized for people with IDD as well.9 It is important to start antidepressants at a low dose and slowly titrate and consider comorbid medical issues and drug-to-drug interactions. Consider utilizing a SSRI as the initial pharmacologic treatment based on their efficacy and tolerability (Figure 1).11 If an SSRI is not appropriate, then consider serotonin-norepinephrine reuptake inhibitors, atypical antidepressants, and serotonin modulators (Figure 1).11 Studies show the efficacy of the various antidepressants as comparable across and within the different classes for both acute and maintenance treatment. The selection of an antidepressant is based on the following: symptoms, comorbid diagnosis, safety, side effect profile, drug-to-drug interaction, patient preference, cost, first-degree relative with a history of a positive response to an antidepressant, and patient’s previous response to medications.11
Some side effects12 to consider when selecting an antidepressant include the following:
- Citalopram: increase in irritability for people with ASD; QT prolongation
- Sertraline: higher rates of diarrhea
- Venlafaxine: more nausea and vomiting
- Bupropion: less sexual dysfunction; contraindicated in eating disorders
- Mirtazapine: greater weight gain, sedating
Tricyclic antidepressants and monoamine oxidase inhibitors are typically not utilized as initial treatment for depression given their more serious side effect profile and elevated risk with overdose.
After initiation of an antidepressant, improvement can be seen in 2-4 weeks. If the person is not improving and tolerating the antidepressant, then titrate the antidepressant in stepwise increments as tolerated up to lowest effective dose.
Key Components in Assessing Depression in People with IDD3,13
- Comprehensive history with self-report when possible, and collateral information including behavioural observations from caregivers, residential staff, day staff, etc.
- Good understanding of individual’s baseline functioning and change from baseline
- What does the individual look like when they are doing well?
- When did they last appear that way?
- Symptoms of depression include 4 or more of the following:
- Depressed mood and/or irritable mood
- Loss of interest or pleasure
- Change in appetite or weight
- Insomnia or hypersomnia
- Psychomotor agitation or retardation
- Fatigue or loss of energy
- Feelings of worthlessness or guilt (people with severe/profound intellectual disability do not have cognitive capacity to display this symptom)
- Decrease in concentration
- Recurrent thoughts of death or suicidal ideation or attempts
- Timeline and Severity
- When did the patient begin having symptoms?
- On a scale of 0-10, how severe are the symptoms with 10 being the worst?
- Previous episodes of mania and depression and response to treatment
- Assess for episodes of mania or hypomania to rule out bipolar disorder
- Comorbid substance use/abuse/dependence
- Assess for psychosocial stressors and abuse
- Family history of mental health issues and suicide attempts or completions
Physical examination: Assess for illnesses that can be associated with depression (e.g., hypothyroidism, epilepsy, stroke, anemia).
Review individual’s medication list. Assess if medications are causing/contributing to depression.
- Ask about complementary and alternative medications.
- Some classes of medication can cause depression (e.g., cardiovascular drugs, chemotherapeutics, antiparkinsonian, anti-infective and antiretroviral agents, anticonvulsants, hormones, antihistamines, and sedatives).
Mental Status Examination: Assess suicidality and homicidality, psychotic symptoms, catatonic symptoms, and future orientation.
Labs to consider: Thyroid stimulating hormone (TSH), complete blood count (CBC), vitamin D level, liver function tests (LFTs), renal function tests.
Treatment Resistance1,12-13
For people not showing improvement with antidepressant treatment, consider re-evaluating their diagnosis and treatment compliance. Switching antidepressants should be considered if symptoms fail to improve after a 6 to 12-week medication trial at a therapeutic dose (see Figure 1). If the individual shows a partial response to treatment, then consider augmenting the initial antidepressant with second-generation antipsychotics (aripiprazole, quetiapine, brexpiprazole, and risperidone), lithium, or other antidepressants. The risks and harms of adding additional medications must be carefully considered. After adequate trials of antidepressants, if the individual continues to have significant symptoms of depression, consider neurostimulation such as repetitive transcranial magnetic stimulation (rTMS) or ketamine/eskatamine, or electroconvulsive therapy (ECT). ECT should only be utilized when symptoms are severe, refractory to medication treatment, or due to intolerable side effects from medications.
Figure 1: Consensus Psychotropic Treatment Algorithm — Depressive Disorders
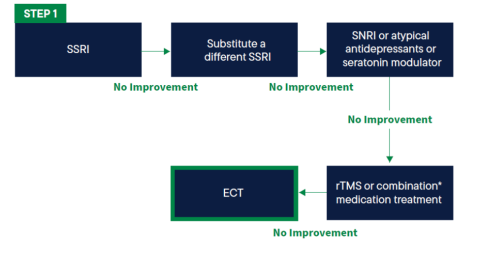
*Combination Medication Treatment with medications that complement each other such as buproprion plus SSRI, TCA plus SSRI
Comorbid Treatment
- For people with severe suicidality or malnutrition secondary to depression and food refusal: consider electroconvulsive therapy.
- For people with psychotic symptoms: add an antipsychotic to antidepressant treatment.
- For people with catatonic features due to depression: add a benzodiazepine to antidepressant treatment.
Vignette
Mr. F is a 28-year-old male with mild ID. When doing well, Mr. F is friendly, funny and enjoys spending time with others. He has been living with a caregiver for the past 5 years. Mr. F’s caregiver scheduled the initial appointment due to a concern that Mr. F does not want to get out of bed in the morning.
At the interview it was reported that Mr. F is pacing more than usual, no longer engages
in his preferred activities, needs more encouragement to do things, is irritable, and makes statements that he is bad, he wishes he were dead or not here. While you didn’t learn about this initially, through additional inquiry about recent stressors, you also learned that there was a recent change in staffing at his day program, and that he has intermittent tearfulness, which is new. Mr. F’s biological family has a history of schizophrenia, depression, and anxiety.
Mr. F is diagnosed with a major depressive disorder. The PHQ-9 completed by Mr. F’s caregiver is consistent with depression. Mr. F is connected to a therapist; however, there is a wait of several weeks to start. In the meantime, Mr. F’s caregiver is encouraged to purposefully schedule enjoyable and meaningful activities in which to engage Mr. F. The caregiver is encouraged to validate the feelings of loss Mr. F is experiencing. Mr. F is started on an SSRI to treat depression. Mr. F begins modified CBT several weeks later. His therapist reviews his previous neuropsychological assessments to target Mr. F’s therapy to his cognitive strengths. Mr. F’s depression resolves in several weeks with combination treatment of SSRI, modified CBT, encouraged engagement, and validation of his feelings regarding losing a preferred staff. He remains on his SSRI for 1 year, and it is slowly tapered with no re-emergence of depressive symptoms.
References
- American Psychiatric Association. Practice Guideline for the Treatment of Patients With Major Depressive Disorder. Washington, DC: American Psychiatric Association; 2010.
- American Psychiatric Association. Diagnostic and Statistical Manual of Mental Disorders. 5th ed, Text Revision (DSM-5-TR). Washington, DC: American Psychiatric Association; 2022.
- Fletcher RJ, Barnhill J, Cooper SA, eds. Diagnostic Manual–Intellectual Disability: A Textbook of Diagnosis of Mental Disorders in Persons With Intellectual Disability. Kingston, NY: NADD Press; 2017.
- Breen J. Adapting the GAD-7 and PHQ-9 Clinical Measures for People With Learning Disabilities [PhD thesis]. London, UK: Royal Holloway, University of London; 2017.
- Anand A, Mathew SJ, Sanacora G, et al. Ketamine versus ECT for nonpsychotic treatmentresistant major depression. N Engl J Med. 2023;388:2315.
- National Collaborating Centre for Mental Health (UK). Depression: The Treatment and Management of Depression in Adults (Updated Edition). Leicester, UK: British Psychological Society; 2010.
- Constantino JN, Strom S, Bunis M, et al. Toward actionable practice parameters for “dual diagnosis”: principles of assessment and management for co-occurring psychiatric and intellectual/developmental disability. Curr Psychiatry Rep. 2020;22(9).
- Cooper SA, Smiley E, Allan L, et al. Incidence of unipolar and bipolar depression, and mania in adults with intellectual disabilities: prospective cohort study. Br J Psychiatry. 2018;212:295-300.
- Cooper SA, Smiley E, Morrison J, et al. Mental ill-health in adults with intellectual disabilities: prevalence and associated factors. Br J Psychiatry. 2007;190:27-35.
- Gartlehner G, Hansen RA, Morgan LC, et al. Comparative benefits and harms of secondgeneration antidepressants for treating major depressive disorder: an updated meta-analysis. Ann Intern Med. 2011;155:772-785.
- Kennedy SH, Lam RW, McIntyre RS, et al. Canadian Network for Mood and Anxiety Treatments (CANMAT) 2016 clinical guidelines for the management of adults with major depressive disorder: Section 3. Pharmacological treatments. Can J Psychiatry. 2016;61:540-606.
- Hamers PCM, Festen DAM, Hermans H. Non-pharmacological interventions for adults with intellectual disabilities and depression: a systematic review. J Intellect Disabil Res. 2018;62:684-700.
- Simon GE, Perlis RH. Personalized medicine for depression: can we match patients with treatments? Am J Psychiatry. 2010;167(1):445-455.
